
II. Indications: Anticoagulation Reversal
- Life Threatening Bleeding in General (see below for life-threatening GI Bleeding)
- Hemodynamic instability (requiring Blood Transfusion or Vasopressors)
- Ongoing Hemorrhage AND
- Hemoglobin drops >=2 g/dl or
- Blood Transfusion of >=2 units pRBC required or
- Surgery or procedural intervention (e.g. Intervention Radiology) required for Hemorrhage Control
- Life threatening Gastrointestinal Bleeding
- Hemodynamic instability
- Vasopressor requirement
- Ongoing Hemorrhage AND
- Hemoglobin drops >=5 g/dl or
- Blood Transfusion of >=5 units pRBC required
- References
- Critical-Site Bleeding
- Intracranial Bleeding
- Spinal canal bleeding (e.g. Epidural Hematoma)
- Ocular or periocular Hemorrhage
- Pericardial Hemorrhage
- Airway compromise due to Hemorrhage (e.g. expanding neck Hematoma)
- Extremity Hemorrhage with risk of Compartment Syndrome
- Intraabdominal Hemorrhage
- Retroperitoneal Hemorrhage
- Intrathoracic Hemorrhage
- Emergent surgery
- Abdominal surgery
- Neurosurgical intervention
III. Physiology
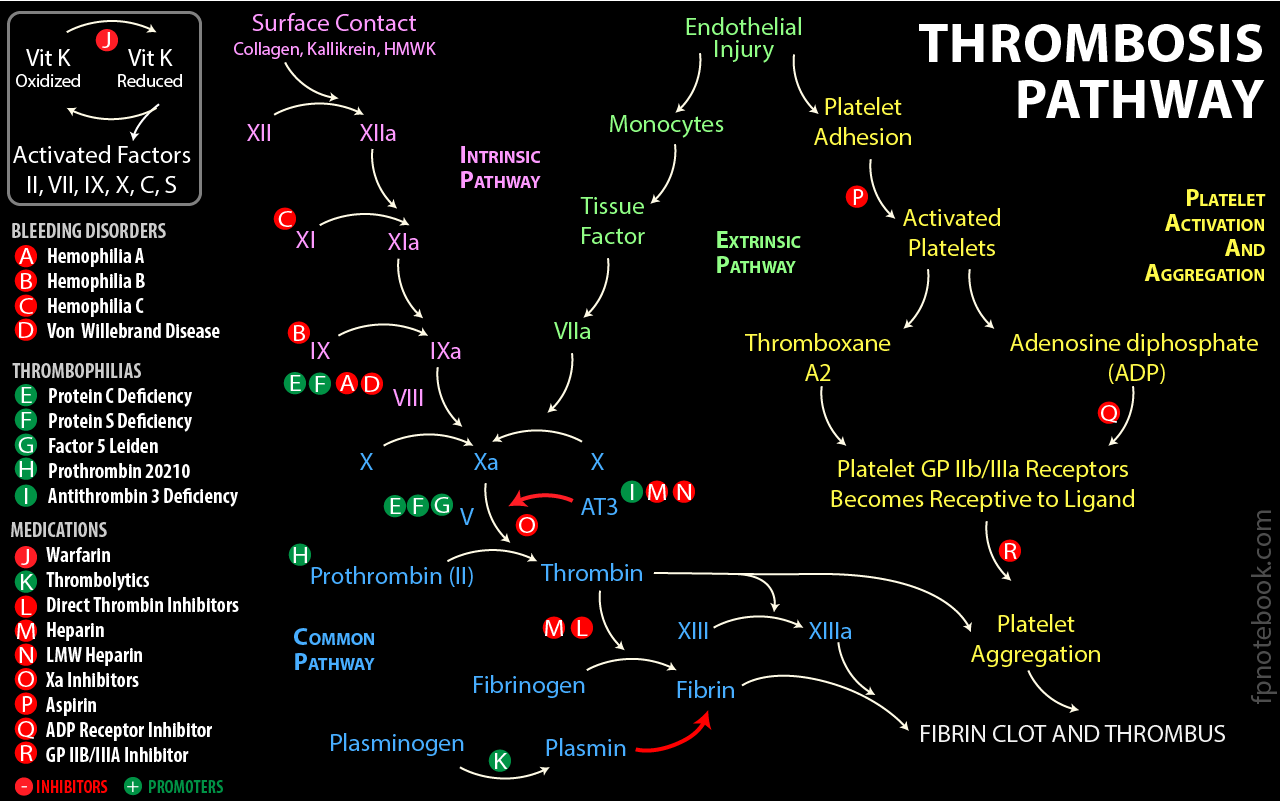
- See Hemostasis
-
Clotting Cascade
-
- Full Thrombosis Pathway

IV. Precautions
- Most reversal agents (PCC, rFVIIa) are thrombogenic and a risk for thromboembolic events
V. Labs
- Degree of Anticoagulation
- Partial Thromboplastin Time (aPTT)
- International Normalized Ratio (INR, PT)
- Anti-Xa (Heparin Level)
- Other labs that impact Anticoagulation and reversal
- Complete Blood Count with Platelet Count
- ABO Type and Rh, Cross Match for Blood
- Serum Creatinine
- Hepatic Panel
- Fibrinogen
VI. Management: General
-
Consultation
- Hematology (if available)
- General surgery
- Intervention Radiology (embolization of bleeding site)
- Control bleeding per specific sites
- Gastrointestinal Bleeding
- Extremity bleeding with Tourniquet
- Facial or scalp bleeding with Suture
- Pelvic Fracture bleeding with Pelvic Binder
- Transfusion
- Correct Anemia (Hemoglobin <7-8) with Packed Red Blood Cells
- Correct Thrombocytopenia with Platelet Transfusion
- Correct other causes of Coagulopathy
- Fresh Frozen Plasma (FFP) is unlikely to correct bleeding due to Anticoagulant medications listed below
-
Overdose
- Consider Activated Charcoal if ingestion within 1-2 hours (may be effective with DOACs up to 8 hours)
- Intentional Overdose
- Observe for bleeding for 24 hours (or per poison control) before medically cleared to psychiatry
- Unintentional Overdose
- If small quantity (e.g. one extra dose) may discharge home with bleeding precautions
- Risk of significant bleeding 5% after Anticoagulant Overdose
- References
- Swaminathan and Hayes in Herbert (2018) EM:Rap 18(7): 4-5
- Levine (2018) Ann Emerg Med 71(3): 273-8 +PMID:29032872 [PubMed]
VII. Management: Reversal of Warfarin and other Vitamin K Antagonists (VKA)
- See Warfarin Reversal
- Mechanism
- Warfarin and VKAs prevent activation of Factors 2, 7, 9 and 10
- Indicated for INR >2.0
- May consider for INR >1.3 to 1.5 with life threatening Hemorrhage (e.g. Intracerebral Hemorrhage)
-
Vitamin K slow IV 2.5-10 mg
- Intravenous route is preferred for active Hemorrhage or hemodynamic instability
- If mild to moderate bleeding, as little as 2.5 mg orally may be effective
- Factor Replacement
- Prothrombin Complex Concentrate 4 (PCC4, Kcentra or outside U.S. Octaplex, Beriplex)
- Preferred if available
- FFP-like serum extract that is 25 fold more potent than FFP
- Dose: 50 Units/kg once daily
- Consider 10-25 Units/kg if INR <2.0
- Fresh Frozen Plasma (FFP)
- Indicated if PCC unavailable
- Slower reversal due to thawing and ABO cross match prior to infusion
- Risk of Fluid Overload (requires larger volume infusions of plasma)
- Factor VIIa (NovoSeven) is no longer recommended
- Prothrombin Complex Concentrate 4 (PCC4, Kcentra or outside U.S. Octaplex, Beriplex)
VIII. Management: Reversal of Heparin (unfractionated and LMWH)
- Mechanism
- See Intrinsic Clotting Pathway
- Heparin binds to, and potentiates Antithrombin III (AT III)
- Antithrombin III binds to and inhibits Serine proteases, Factor IIa (Thrombin) and Factor Xa
- Antithrombin III also binds to and inhibits Factors IXa, XIa and XIIa
- Results in decreased Fibrin formation
- Unfractionated Heparin
- Composed of Polysaccharides of various lengths, resulting in less predictable Pharmacokinetics, requiring close monitoring
- Heparin also transiently interacts with Thrombin, independent of its action via Antithrombin 3
- Low Molecular Weight Heparin (LMHW, Enoxaparin)
- LMHW is a small fragment of the larger Heparin molecule (mucopolysaccharide)
- Allows for more predictable Pharmacokinetics, and fewer complications (bleeding, HIT)
-
Unfractionated Heparin Reversal
- Stop Heparin infusion
- Short Heparin Half-Life 40-90 minutes results in rapid reversal of Anticoagulation on stopping infusion
- Additional reversal agents are rarely needed
- Protamine Sulfate (preferred first-line)
- See Protamine for dosing details
- Give 1 mg Protamine sulfate for every 100 units of Unfractionated Heparin administered within prior 2-3 hours
- Administer slowly (no more than 50 mg per 10 minute interval) to prevent Hypotension, Anaphylaxis-like reaction
- Stop Heparin infusion
-
Low Molecular Weight Heparin (LMWH, Enoxaparin)
- Background
- LMWH half life is 4 hours (more likely to require reversal than Unfractionated Heparin)
- Prothrombin Complex Concentrate 4 (PCC4, Kcentra or outside U.S. Octaplex, Beriplex)
- First-line agent for LMWH
- Protamine Sulfate (second-line)
- In contrast with Unfractionated Heparin, Protamine only partially reverses LMWH
- Administer slowly (no more than 50 mg per 10 minute interval) to prevent Hypotension, Anaphylaxis-like reaction
- Give 1 mg for every 1 mg (100 units) Enoxaparin in <8 hours
- Give 0.5 mg for every 1 mg (100 units) Enoxaparin in >8 hours
- Background
IX. Management: Reversal of Factor Xa Inhibitors (e.g. Rivoroxaban or Xarelto, Apixaban or Eliquis)
- Mechanism: Factor Xa Inhibitors
- Directly and reversibly bind the active site on Factor Xa
- Block Thrombin formation as a part of the Common Clotting Pathway
- Mechanism: Indirect Xa Inhibitors (e.g. Fondaparinux)
- Binds Antithrombin III and modifies its form, substantially increasing its activity by 300 fold
- Super-charged Antithrombin III neutralizes Factor Xa at a markedly increased rate, resulting in Anticoagulation
- Reversal General Guidelines
- Stop offending Xa agent (most have half-lives of 12 hours)
- Bleeding unlikely due to Xa agent if Anti-Xa level <0.1 IU/ml
- Hemodialysis is not effective (Protein bound, unlike Dabigatran)
- Reversal in Life threatening or critical site bleeding
- Step 1
- Prothrombin Complex Concentrate 4 (PCC4, Kcentra or outside U.S. Octaplex, Beriplex)
- Dose 25 to 50 units/kg IV using actual weight, and contingent on bleeding severity
- Maximum dose: 2500 to 5000 units
- Alternative Agents if PCC4 not available
- PCC3 or
- Fresh Frozen Plasma (FFP)
- Prothrombin Complex Concentrate 4 (PCC4, Kcentra or outside U.S. Octaplex, Beriplex)
- Step 2 (if no response to step 1)
- Consult Hematology
- Consider repeat dosing of agents as above
- Other agents previously used
- Factor VII Inhibitor Bypass Activity (FEIBA) 50-75 units/kg IV once (up to maximum 7500 units)
- Consider Recombinant activated Clotting Factor VII (rFVIIa or NovoSeven)
- Dose: 90 mcg/kg IV once (up to maximum 10 mg)
- Improves lab data, but not effective in animal models
- Step 1
- Agents not recommended or unavailable
- Andexxa or Andexanet Alpha
- Released in 2018, and off U.S. market in 2025
- Inactivated Recombinant Factor Xa decoy Protein
- Dosing based on Factor Xa Level (use high dose if Xa level unknown)
- Low Dose: 400 mg IV bolus over 14 min, then 480 mg infusion over 120 min
- High Dose: 800 mg IV bolus over 28 min, then 960 mg infusion over 120 min
- Cost approaches $30,000 to 50,000 per dose
- Ineffective in the 25% of patients who have low anti-Factor Xa Inhibitor
- Connolly (2019) N Engl J Med 380(14):1326-35 +PMID:30730782 [PubMed]
- Andexxa or Andexanet Alpha
X. Management: Reversal of Direct Thrombin Inhibitors (e.g. Dabigatran)
- Mechanism: Direct Thrombin Inhibitors
- Selectively and reversibly inhibit free and clot-bound Thrombin
- Prevent conversion of Fibrinogen to Fibrin (which in turn prevents clot)
- Reversal General Guidelines
- Stop offending agent (most have short Half-Life such as 12-14 hours for Dabigatran)
- Bleeding unlikely due to Direct Thrombin Inhibitor if aPTT <37 seconds and Thrombin Time <25 seconds
- Consider Activated Charcoal if presenting within 2 hours of suspected Overdose ingestion
- Hemodialysis is unlikely to be beneficial
- Risk of placing large bore filtered catheters in actively bleeding, coagulopathic patients
- Reversal in Life threatening or critical site bleeding
- Step 1 (choose 1)
- Idarucizumab (preferred)
- Monoclonal Antibody specific for Dabigatran
- Highly effective in initial studies and FDA approval (however may not alter clinical outcomes)
- Give 2 doses each of 2.5 g IV
- Follow Thrombin Time and PTT
- Pollack (2015) N Engl J Med 373(6): 511-20 +PMID: 26095746 [PubMed]
- Pollack (2017) N Engl J Med 377(5): 531-41 +PMID: 28693366 [PubMed]
- Alternatives if Idarucizumab is not available
- Prothrombin Complex Concentrate 4 (PCC4, Kcentra or outside U.S. Octaplex, Beriplex) OR
- Fresh Frozen Plasma (FFP)
- Cryoprecipitate (from FFP)
- Idarucizumab (preferred)
- Step 2 (if no response to step 1)
- Consult Hematology
- Hemodialysis increases clearance (limited benefit)
- Consider repeat dosing of agents in step 1
- Consider Desmopressin (DDAVP) 0.3 mcg/kg (if on antiplatelet agents)
- Other agents previously used
- Factor VII Inhibitor Bypass Activity (FEIBA) 50 units/kg IV once (up to 7500 units)
- Activated Clotting Factor VII (rFVIIa or NovoSeven) 90 mcg/kg IV once (up to 10 mg)
- Step 1 (choose 1)
XI. Management: Reversal of Antiplatelet Agents
-
Aspirin
- Mechanism
- Aspirin irreversibly inactivates cyclooxygenase (COX)
- Blocks Thromboxane and Prostaglandin synthesis
- Contrast with NSAIDS which reversibly block COX
- Platelet Effects (Thromboxane-related)
- Inhibits Platelet aggregation via cyclooxygenase blockade of Thromboxane A2 synthesis
- Aspirin Irreversibly poisons Platelets for their remaining life (8-10 days)
- New Platelets are generated at a rate of 10% per day (25,000/day for a patient with a 250,000 Platelet Count)
- Aspirin irreversibly inactivates cyclooxygenase (COX)
- Reversal
- Platelet Transfusion 1 unit (6 pack) for high risk perioperative reversal (e.g. neurosurgery for Intracerebral Hemorrhage)
- Consider Desmopressin (DDAVP) 0.3 mcg/kg (expert opinion)
- Consider Recombinant activated Clotting Factor VII (rFVIIa) 30-90 mcg/kg (expert opinion)
- Mechanism
- ADP Inhibitors (Thienopyridine Class, e.g. Clopidogrel)
- Mechanism
- Inhibits Platelet signal transduction
- Inhibits Platelet aggregation
- Reversibly binds Adenosine Diphosphate (ADP) P2Y12-Class Receptors (inhibits G-Protein, Adenyl cyclase)
- Reversal
- Platelet Transfusion 2 units (12 pack)
- Consider Desmopressin (DDAVP) 0.3 mcg/kg (expert opinion)
- Consider Recombinant activated Clotting Factor VII (rFVIIa) 30-90 mcg/kg (expert opinion)
- Mechanism
XII. Management: Reversal of Thrombolytic (Tissue Plasminogen Activator or tPA, TNK-tPA or Tenecteplase)
- Mechanism
- Serine protease binds Fibrin and activates Fibrin-bound plasminogen to plasmin
- Plasmin breaks down both Fibrin and Fibrinogen to Fibrin
- Fibrin Degradation Products result, which in turn also act to inhibit Fibrin formation
- Reversal
- Not reduced by clot-specific agents
- Consider infusing Fibrinogen Concentrate or Cryoprecipitate 10 pack
- Consider Fresh Frozen Plasma
- Consider Tranexamic Acid (TXA)
- References
- Swaminathan and Weingart in Herbert (2020) EMRap 20(4):5-6
XIII. Resources
- ACEP: Reversal of NOACs in the Presence of Major Life-Threatening Bleeding
XIV. References
- Clemens and Oliver (2026) Crit Dec Emerg Med 40(10): 27-37
- Deloughery and Orman in Herbert (2013) EM:Rap 13(9): 1
- Ebersole, Toomey and Baugh (2021) Crit Dec Emerg Med 35(5): 3-9
- Lex and Orman in Herbert (2013) EM:Rap 13(4): 6
- Lemkin (2013) Crit Dec Emerg Med 27(4): 2-9
- Marcolini and Swaminathan in Swadron (2023) EM:Rap 23(3): 3-6
- Sun (2016) Crit Dec Emerg Med 30(8): 28
- Umoga and Eyre (2023) Crit Dec Emerg Med 37(10): 14-5
- Peck (2021) J Trauma Acute Care Surg 90(2): 331-6 [PubMed]